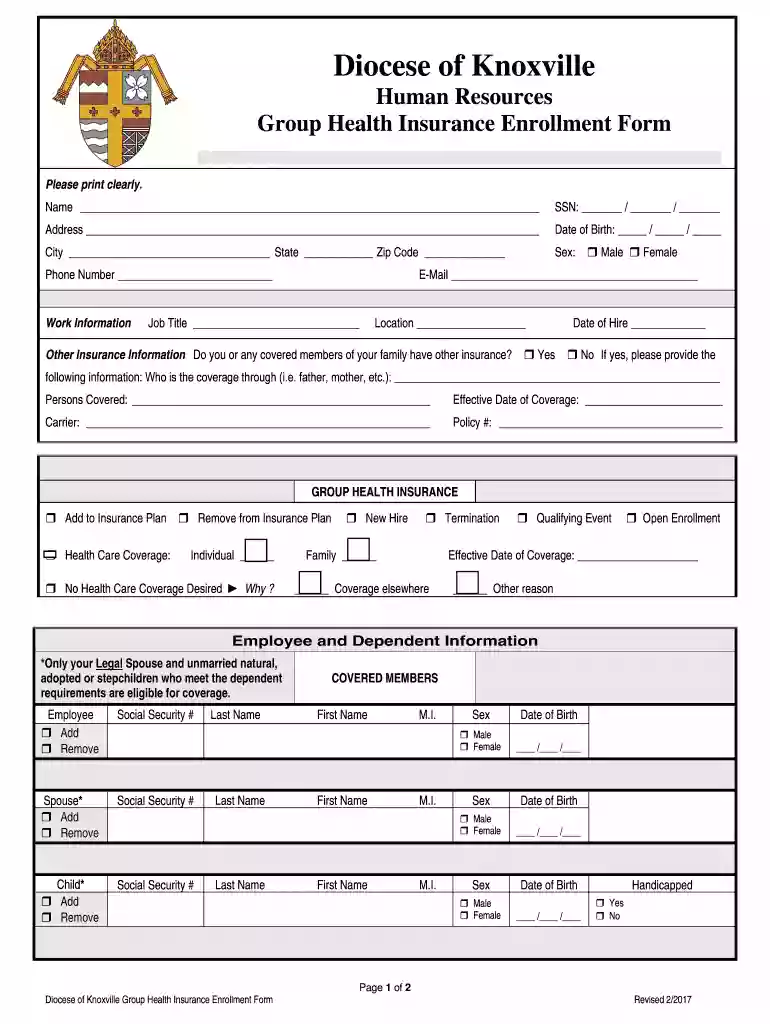
medical enrollment form Preview on Page 1

Group Health Insurance Enrollment Form 2026

Here's how it works

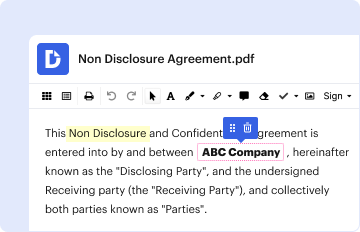
  • 01. Edit your medical enrollment form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

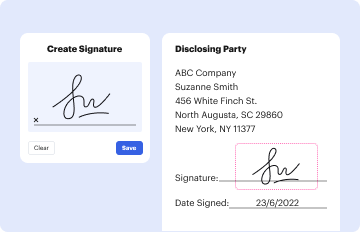
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out Group Health Insurance Enrollment Form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the Group Health Insurance Enrollment Form in the editor.
  2. Begin by filling in your personal information at the top of the form. Clearly print your name, Social Security Number, address, date of birth, and contact details.
  3. In the Work Information section, provide your email, job title, location, and date of hire. This information is essential for processing your enrollment.
  4. Next, indicate if you or any family members have other insurance coverage by selecting 'Yes' or 'No.' If 'Yes,' provide details about the coverage provider and policy number.
  5. Choose whether to add or remove yourself from the insurance plan and specify if you are enrolling due to a qualifying event or during open enrollment.
  6. Complete the Employee and Dependent Information section by adding details for each dependent you wish to enroll. Ensure all names and Social Security Numbers are accurate.
  7. Finally, review your entries for accuracy before signing and dating the form at the bottom. This confirms your understanding of pre-tax contributions.

Start using our platform today to easily complete your Group Health Insurance Enrollment Form online for free!

See more medical enrollment form versions

We've got more versions of the medical enrollment form form. Select the right medical enrollment form version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20224.2 Satisfied (60 Votes)
20214.8 Satisfied (43 Votes)
20174.6 Satisfied (23 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

Group Health Insurance Application for Special Enrollment

Verification of Coverage. Please complete all of the information below. Return this form with a: 1) Benefits Enrollment/Change Form and, 2) your. CertificateRead more

Learn more
HEALTH BENEFITS ENROLLMENT and/or CHANGE FORM

GROUP HEALTH BENEFITS ENROLLMENT and/or CHANGE FORM HA-0891-0619. You must provide proof of the loss of other coverage and submit it with your application

Learn more
SGLV 8714, Application for Veterans Group Life Insurance

Veterans Group Life Insurance Application Instructions. You have one year and 120 days from your date of separation to apply for Veterans.Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here