





Here's how it works
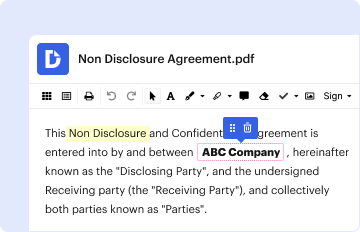
01. Edit your tenncare appeal online
Type text, add images, blackout confidential details, add comments, highlights and more.
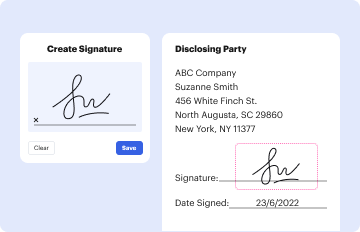
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Claims, Appeals & Provider Complaints with our platform

- Click ‘Get Form’ to open it in the editor.
- Begin by entering the personal details of the person appealing. Fill in their full name, date of birth, Social Security Number or TennCare card number, and current mailing address.
- Indicate who is filling out the form. If it's not the person appealing, provide your name and select your relationship to the individual (e.g., parent, advocate).
- Specify the reason for the appeal by placing an X next to one of the options: changing health plans, needing care or medicine, or disputing bills.
- If applicable, indicate whether you believe there is an emergency situation that requires an expedited appeal. Follow instructions for obtaining necessary permissions if a doctor is involved.
- In the provided sections (Parts A, B, C), detail your specific appeal reasons and include any relevant documentation that supports your case.
- Once completed, make a copy of all pages for your records before submitting them via mail or fax as instructed.
Start using our platform today to streamline your Claims, Appeals & Provider Complaints process for free!
Fill out Claims, Appeals & Provider Complaints online
It's free
It's free
See more Claims, Appeals & Provider Complaints versions
We've got more versions of the Claims, Appeals & Provider Complaints form. Select the right Claims, Appeals & Provider Complaints version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


