




Here's how it works
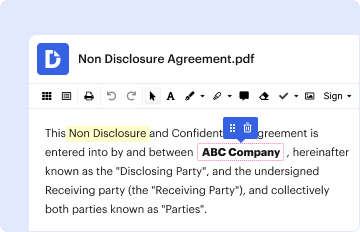
01. Edit your advocate medical records release form online
Type text, add images, blackout confidential details, add comments, highlights and more.
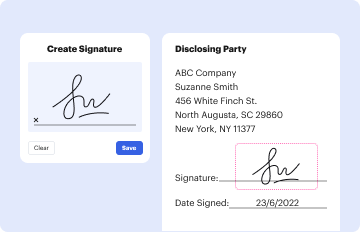
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
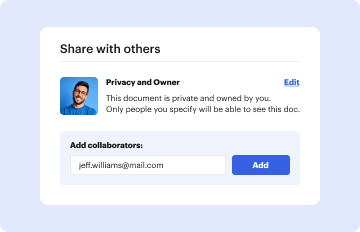
03. Share your form with others
Send release of information form advocate via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out advocate dreyer medical clinic release of information fax

- Click ‘Get Form’ to open it in the editor.
- Begin by filling in your personal details: enter your name, street address, city, state, zip code, phone number, date of birth, and medical record number. Ensure accuracy for a smooth processing.
- In the authorization section, specify the person or organization from whom you are requesting information. Fill in 'DREYER MEDICAL CLINIC' as the source and provide the recipient's details accurately.
- Indicate the purpose for requesting this information by selecting 'FOR DISCOVERY BEFORE TRIAL' and check all applicable types of health information you wish to disclose.
- If there are any specific types of health information you do not want released, check those boxes accordingly.
- Sign and date the form at the bottom. If applicable, include the signature of a parent or legal guardian along with their relationship to you.
Start using our platform today to easily complete your advocate dreyer medical clinic release of information fax for free!
Fill out advocate dreyer medical clinic release of information fax online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


