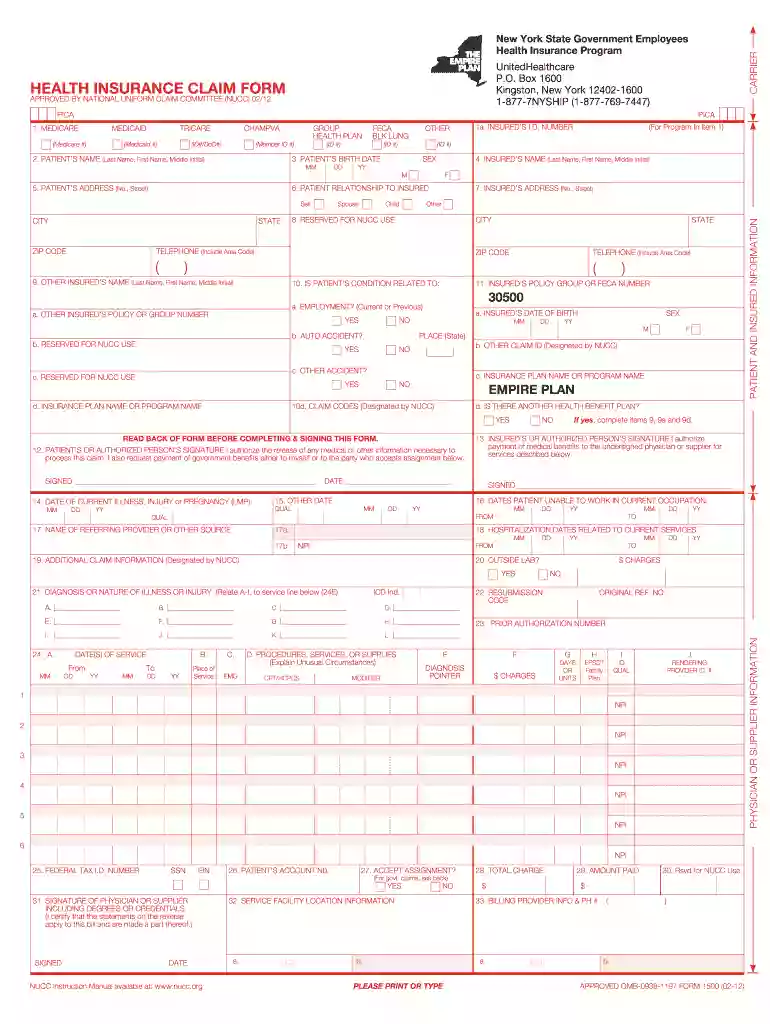
nyship claim form Preview on Page 1

Nyship claim form 2026

Here's how it works

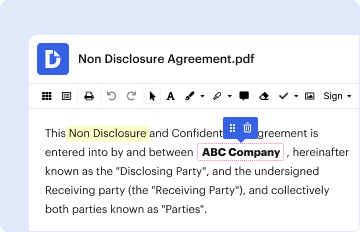
  • 01. Edit your nyship claim form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

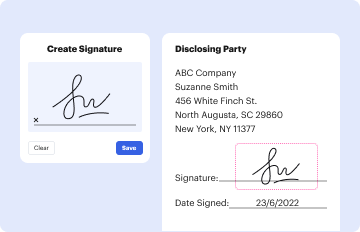
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
  • 03. Share your form with others

    Send nyship out of network claim form via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out nyship claim form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the nyship claim form in the editor.
  2. Begin by filling in the patient’s name (Last, First, Middle Initial) in section 2. Ensure accuracy as this is crucial for processing your claim.
  3. In section 4, enter the insured's name and relationship to the patient. This helps identify who holds the insurance policy.
  4. Complete sections 5 and 7 with the patient's and insured's addresses, including city, state, and zip code. This information is essential for correspondence.
  5. Fill out section 10 regarding any related conditions to ensure all necessary details are captured for your claim.
  6. Sign and date where indicated in sections 12 and 13 to authorize payment of benefits and release of medical information.

Start using our platform today to fill out your nyship claim form easily and for free!

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

nyship

Empire Plan Claim Form

HEALTH INSURANCE CLAIM FORM. 1. MEDICARE. MEDICAID. CHAMPUS. CHAMPVA. GROUP. FECA PLEASE MAIL CLAIMS TO: United HealthCare Insurance Company of New York.Read more

Learn more
health insurance claim form - NYS Department of Civil Service

INSUREDS OR AUTHORIZED PERSONS SIGNATURE I authorize payment of medical benefits to the undersigned physician or supplier for services described below. SIGNED.Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here