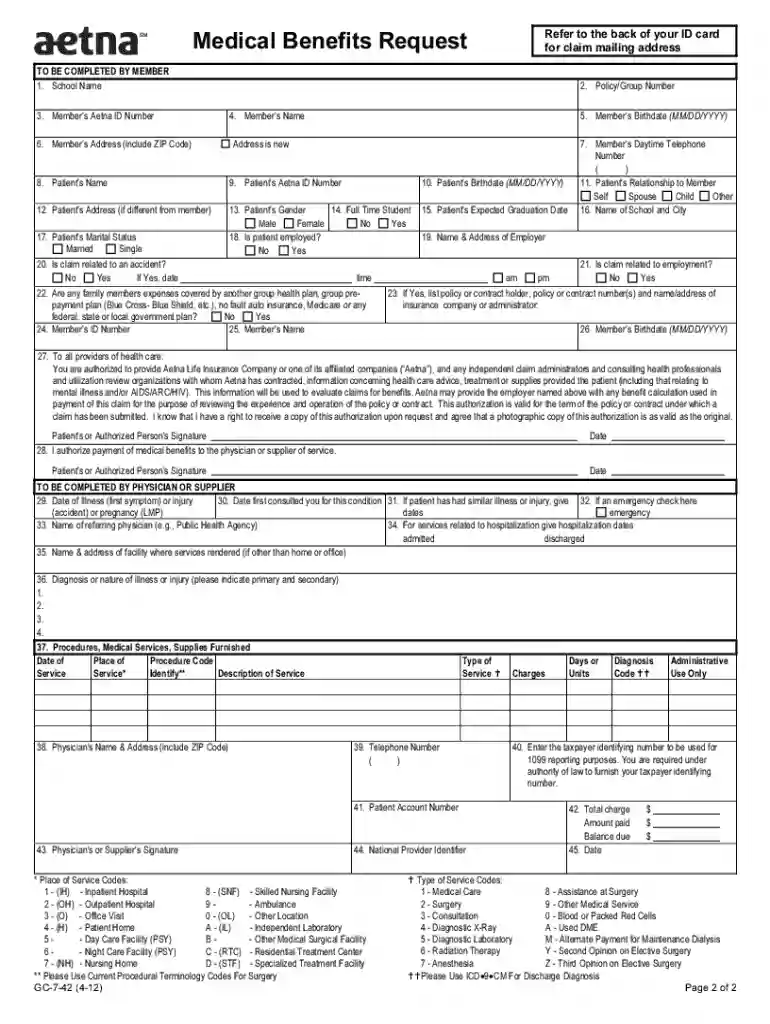
aetna medicare reimbursement form Preview on Page 1

Medical forms aetna 2026

Here's how it works

  • 01. Edit your aetna medicare reimbursement form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
  • 03. Share your form with others

    Send aetna via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out medical forms Aetna with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the medical forms Aetna in the editor.
  2. Begin by completing items one (1) through twenty-one (21) thoroughly. Ensure all personal information, such as your name, address, and Aetna ID number, is accurate.
  3. If applicable, fill out items twenty-two (22) through twenty-six (26) regarding any other medical coverage you may have.
  4. Sign the authorization to release information in block twenty-seven (27). This is crucial for processing your claim.
  5. If you want benefits paid directly to your physician or supplier, sign block twenty-eight (28).
  6. Attach itemized bills from your healthcare provider that include necessary details like patient’s name and service dates. If prescription drugs are involved, submit receipts with required information.
  7. Review all entries for completeness before submitting. Incomplete forms will delay processing.

Start using our platform today for free to streamline your medical form submissions effortlessly!

See more aetna medicare reimbursement form versions

We've got more versions of the aetna medicare reimbursement form form. Select the right aetna medicare reimbursement form version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20164.8 Satisfied (106 Votes)
20124.2 Satisfied (47 Votes)

be ready to get more

Complete this form in 5 minutes or less

Got questions?

We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.

Go to .aetna.com. Select Register Now in the Members: Secure Information section. Select View your Personal Health Record Follow the links and instructions on sharing your PHR.
You can use your card at all these locations: Walmart, Walgreens,cvs, dollar general !
Form 1095-A (Health Insurance Marketplace Statement) This form shows how much your health plan costs and the tax credits you received. Its mailed to you in February.
With the card, you can buy certain over-the-counter items listed in your OTC catalog. If you have a Dual Special Needs Plan, youll also have access to an Extra Benefits Card. With this card, you can pay for everyday expenses like approved groceries, OTC items, rent/utilities, and transportation.
The Health Insurance Claim Form (CMS-1500) is used by Allied Health professionals, physicians, laboratories and pharmacies to bill supplies and services to the Medi-Cal program. Providers are required to purchase CMS-1500 claim forms from a vendor.

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

People also ask

Members in these plans who qualify for Extra Help get an Extra Benefits Card with an allowance to help pay for approved everyday expenses including over-the-counter products, healthy foods, personal care products, utilities and gas or transportation. Could you use additional support? Learn more today.

aetna medical benefits request

Washington Medical Equipment

Dec 31, 2020 If you sign a written authorization allowing us to disclose medical information about you, you may later revoke (or cancel) your authorizationRead more

Learn more
Aetna - Medical Benefits Claim Form Instructions

Medical Benefits Request Mail to: Aetna Life Insurance Company. PO Box 981106. El Paso, TX 79998-1106. TO BE COMPLETED BY EMPLOYEE. 1. Employers Name. 2.Read more

Learn more
Aetna Medical Claim Form

aetna Medical Benefits Request. IRefer to the back of your ID card for claim mailing address. TO BE COMPLETED BY EMPLOYEE. 1. Employers Name. 2. Policy/GroupRead more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here