




Here's how it works
01. Edit your wi workforce online
Type text, add images, blackout confidential details, add comments, highlights and more.
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
03. Share your form with others
Send compensation workforce via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out wkc 16 b with our platform

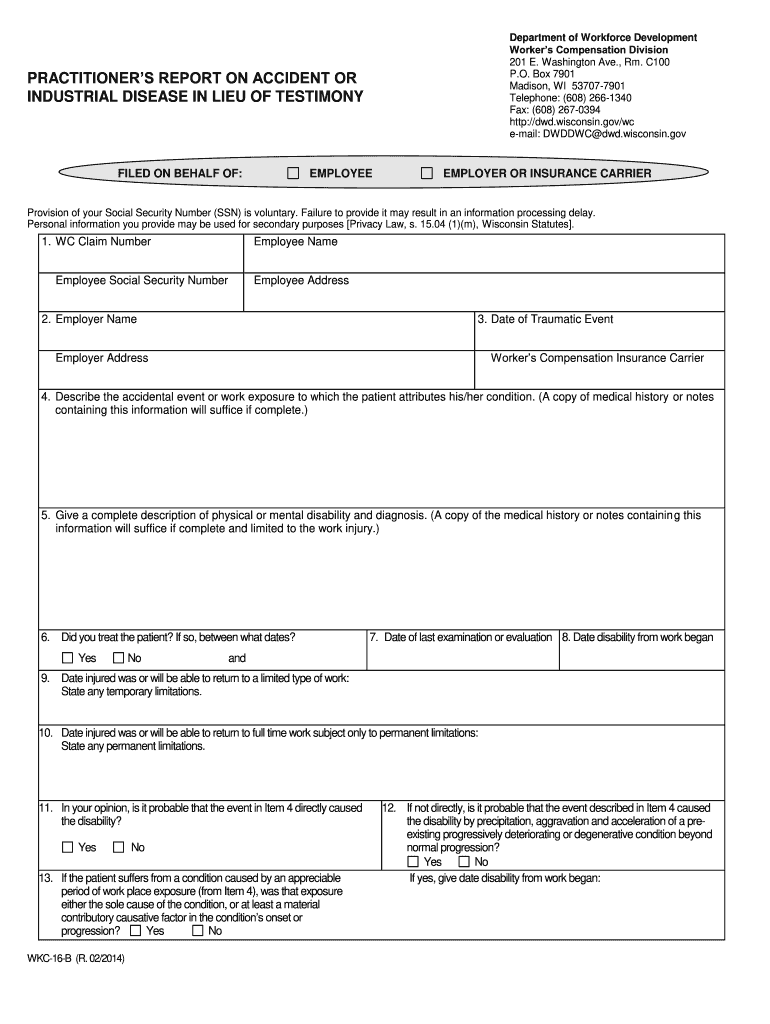
- Click ‘Get Form’ to open the wkc 16 b in the editor.
- Begin by entering the WC Claim Number, Employee Name, and Employee Social Security Number in the designated fields. Remember, providing your SSN is voluntary.
- Fill in the Employer Name and their address. This information is crucial for processing your claim.
- In section four, describe the accidental event or work exposure that led to the condition. You can attach a copy of medical history if it contains this information.
- Provide a detailed description of any physical or mental disabilities and diagnoses related to the work injury in section five.
- Indicate whether you treated the patient and specify treatment dates if applicable.
- Complete sections regarding return-to-work dates and any limitations. Be thorough to ensure accurate processing.
- Finally, certify your report by signing and dating it at the bottom of the form before submitting it through our platform.
Start filling out your wkc 16 b form online for free today!
Fill out wkc 16 b online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


