




Here's how it works
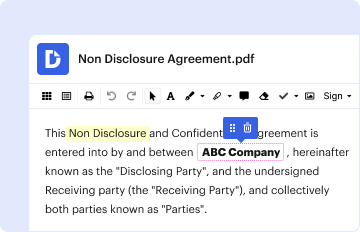
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
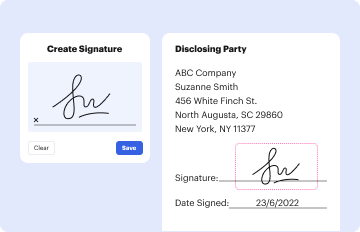
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
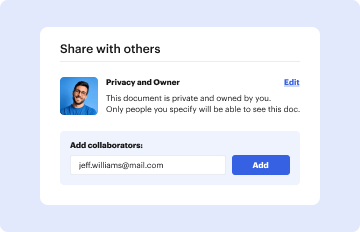
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out certification initial with our platform

- Click ‘Get Form’ to open the certification initial in the editor.
- Begin by entering your PROVIDER NAME and DATE PREPARED at the top of the form. Ensure that these details are accurate for proper identification.
- Fill in your TAX ID and HEALTH PLAN PROVIDER #, followed by your TELEPHONE #. This information is crucial for communication regarding your claim.
- Next, provide MEMBER NAME, DOS (Date of Service), MEMBER ID #, and PATIENT ACCOUNT #. Each field must be completed to ensure a smooth reconsideration process.
- In the PROVIDER COMMENTS section, add any relevant notes that may assist in the reconsideration review.
- Select the REASON FOR CONSIDERATION by checking the appropriate box and attach any necessary documentation as specified.
- Finally, submit the completed form to the Claims Department at Geisinger Health Plan using the provided address.
Start using our platform today to streamline your document editing and submission process for free!
Fill out certification initial online
It's free
It's free
See more certification initial versions
We've got more versions of the certification initial form. Select the right certification initial version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


Related forms

Not Guilty Plea doc
The document is a NOT GUILTY plea form for the City of Lake Geneva Municipal Court in Wisconsin. It allows individuals t ...

Text structure gallery walk
The document outlines a teaching unit designed by Barb Yardley, M.Ed, focused on reading and writing through a 'Gallery ...

How to fill up dole akap form online
The document outlines the application process for financial assistance under the 'DOLE-AKAP for OFWs' program, aimed at ...

Fall Ladies Retreat Registration Form
The document is a registration form for the Fall Ladies Retreat organized by the Independent Fundamental Baptist Fellows ...

APPLICATION FOR MERCHANT SECURITY GUARD
The document is an application form for a Merchant Security Guard License issued by the City Clerk's Office in Salina, K ...

DocHub 528626819--PLEASE-NOTE-OnlyFillable Online PLEASE NOTE: Only use this form for reporting
DocHub 528626819--PLEASE-NOTE-OnlyFillable Online PLEASE NOTE: Only use this form for reporting
The document is a confidential morbidity report form from the California Department of Public Health specifically for re ...

Supreme Court Rules 1937 Form 5 1 - ACT Legislation Register - legislation act gov
The document is a certificate of noncompliance with a subpoena issued by the Supreme Court of the Australian Capital Ter ...


