




Here's how it works
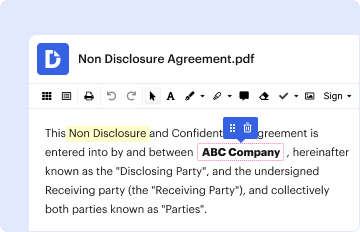
01. Edit your form or ps online
Type text, add images, blackout confidential details, add comments, highlights and more.
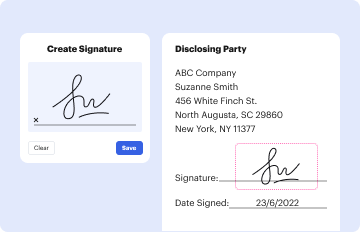
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
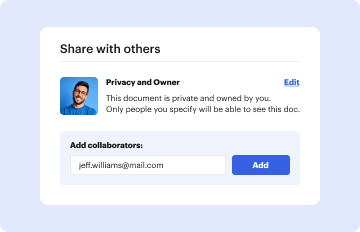
03. Share your form with others
Send provider statement via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Form OR-PS, Care Provider Statement, 150-101-190 with our platform

- Click ‘Get Form’ to open it in the editor.
- Begin by entering the taxpayer's name(s) and Letter ID at the top of the form. If you don't have a Letter ID, input your Social Security Number instead.
- Fill in the date range for the care provided, specifying both start and end dates.
- In the provider section, enter your name along with your Social Security Number (SSN), Individual Tax Identification Number (ITIN), or Federal Employer Identification Number (FEIN).
- List each dependent's name and age, along with total payments received from the taxpayer for each dependent. Include any payments received from third parties as applicable.
- Complete the additional questions regarding payment frequency and methods. Ensure to provide accurate details about receipts issued for payments.
- Sign and date the form at the bottom, confirming that all information is true and complete before submitting it back to the taxpayer or directly to the department.
Start using our platform today to easily fill out and manage your forms online for free!
Fill out Form OR-PS, Care Provider Statement, 150-101-190 online
It's free
It's free
See more Form OR-PS, Care Provider Statement, 150-101-190 versions
We've got more versions of the Form OR-PS, Care Provider Statement, 150-101-190 form. Select the right Form OR-PS, Care Provider Statement, 150-101-190 version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


Related forms

Fillable Online Iowa Department of Revenue Statement of Rent Paid
The document is a form for reporting rent paid in Iowa, intended for individuals who have lived in multiple rental locat ...

Commercial Plumbing Inspection District Map - Dsps wi
The document outlines the procedures and requirements for testing cross connection control devices in Wisconsin, specifi ...

APPLICATION FOR IDENTITY CARD FOR PERSON DEEMED
The document is an application form for obtaining a National Turks and Caicos Islander Status Card, detailing the requir ...

How to get our Marriage Licenses in New Brunswick
The document is an application form for obtaining a marriage certificate in New Brunswick. It outlines the steps for pro ...

Permanent residence fee form
The document is a loan application form for the Right of Permanent Residence Fee (RPRF) provided by Citizenship and Immi ...

Wife addicted to evony and unable to see the damage it's
The document is a sponsorship form for the Shine Night Walk, aimed at raising funds for Cancer Research UK. It encourage ...

Bank of india deposit slip fillable
The document is a form related to the Public Provident Fund Scheme, 1968, designed for subscribers to record their depos ...

Minnesota Uniform Conveyancing Blanks Form 50 1 1 - Justia
This document is an affidavit regarding the purchaser of a property in Minnesota, confirming the legal status and backgr ...