




Here's how it works
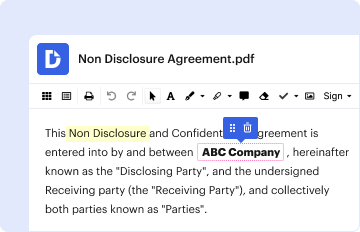
01. Edit your delta dental claim form online
Type text, add images, blackout confidential details, add comments, highlights and more.
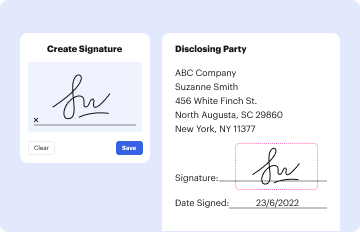
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
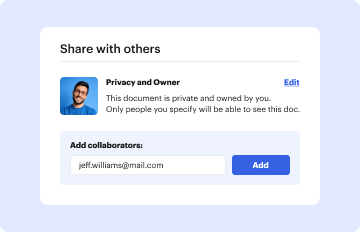
03. Share your form with others
Send delta dental claim form pdf via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out delta dental claim form with our platform

- Click ‘Get Form’ to open the delta dental claim form in the editor.
- Begin by filling out the Subscriber Information section. Enter the Policyholder's name, address, and date of birth accurately. Ensure you include the correct Policyholder ID.
- In the Treatment Information section, indicate if the treatment is due to an accident and provide relevant dates. If orthodontic treatment is involved, complete additional fields regarding appliance placement.
- Complete the Patient Information section with details about the patient, including their relationship to the policyholder and any other insurance coverage they may have.
- Fill in the Record of Services Provided section by detailing each procedure performed, including dates, codes, and fees associated with each service.
- Finally, review all information for accuracy before signing in the Authorization section. Ensure that both subscriber and treating dentist signatures are included.
Start using our platform today to easily fill out your delta dental claim form online for free!
Fill out delta dental claim form online
It's free
It's free
See more delta dental claim form versions
We've got more versions of the delta dental claim form form. Select the right delta dental claim form version from the list and start editing it straight away!
| Versions | Form popularity | Fillable & printable |
|---|---|---|
| 2011 | 4.8 Satisfied (23 Votes) |
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


Related forms

Staff Employee Performance Evaluation Form 138
The document is an HR Form 138 used for evaluating staff employee performance across various units represented by differ ...

Instructions for Annual Transmittal of State 1099 Forms
The document provides instructions for filing the DR 1106 Annual Transmittal of State 1099 Forms with the Colorado Depar ...

Texas Playground Safety Standards Form - Fill Out and
The document is a maintenance checklist for playground safety, outlining various inspection criteria to ensure the safet ...

Dodgeball Waiver Form - bwpcschoolsbborgb
The document is a Dodgeball Waiver Form that requires participants to provide personal information and acknowledges the ...

Ssa-711
The document is Form SSA-711, a request form from the Social Security Administration for obtaining a deceased individual ...

Discharge Summary
The document is a Discharge Summary for a client who has completed a treatment program. It includes details such as the ...

Form H1113
Form H1113 is an application for prior Medicaid coverage, allowing individuals to seek assistance for unpaid medical bil ...

Time Temperature Food Preparation Log
The document is a Time/Temperature Food Preparation Log designed to track the temperature of food items at regular inter ...