




Here's how it works
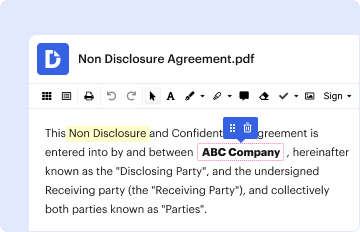
01. Edit your dochub com fillable form online
Type text, add images, blackout confidential details, add comments, highlights and more.
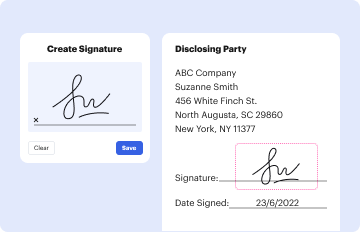
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
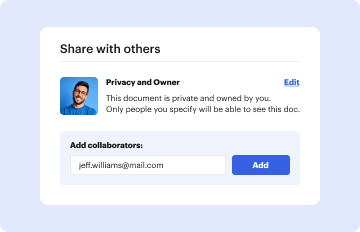
03. Share your form with others
Send cms l564 form via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out 2000 form cms l564 with our platform

- Click ‘Get Form’ to open the 2000 form cms l564 in the editor.
- Begin by entering the claimant's information, including their name and Social Security Number in the designated fields.
- Provide the employer’s name and address at the top of the form, ensuring accuracy for effective communication.
- Answer question 1 regarding whether the claimant is covered under an Employer Group Health Plan by selecting 'Yes' or 'No'.
- If applicable, fill in the original date coverage began in mm/yyyy format.
- Indicate if the coverage has ended by selecting 'Yes' or 'No', and if yes, provide the end date in mm/yyyy format.
- Document the employment period by filling in the start date and checking if still employed.
- Finally, ensure that a company official signs and dates the form before submission.
Start using our platform today to easily complete your forms online for free!
Fill out 2000 form cms l564 online
It's free
It's free
See more 2000 form cms l564 versions
We've got more versions of the 2000 form cms l564 form. Select the right 2000 form cms l564 version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


Related forms

Unit 41 Test Review Thermal Energy Transfer - SharpSchool
The document is a test review focused on thermal energy transfer, covering the methods of conduction, convection, and ra ...
Housekeeping plan for construction site pdf
The document is a Construction Site Housekeeping Checklist from The Hanover Insurance Group, aimed at promoting safety a ...

Certificate of Dependent Eligibility Attestation
The document is a Certificate of Dependent Eligibility Attestation, which requires employees to verify their dependents ...

Mtis Nation of OntarioRegistryMtis of Ontario - Metis
The document provides guidelines for completing a genealogical chart required for citizenship applications with the Méti ...

DS-115 Used by out-of-state drivers to request restoration of their New York State driving privilege
DS-115 Used by out-of-state drivers to request restoration of their New York State driving privilege
The document is a request form for obtaining clearance for New York State driving privileges, requiring personal informa ...

2023 Form OH BMV 4826 Fill Online, Printable, Fillable, Blank
The document outlines the application process for removable windshield placards in Ohio for individuals with disabilitie ...

0) SOURCE OF MATERIAL Name and Location of plant which produces material for Item AA: d) EXACT - sta
0) SOURCE OF MATERIAL Name and Location of plant which produces material for Item AA: d) EXACT - sta
The document is empty and contains no content to summarize.

REVOKED PERMIT NUMBER(S P-61-85 - state wv
The document appears to be empty or contains no discernible content to summarize.