





Here's how it works
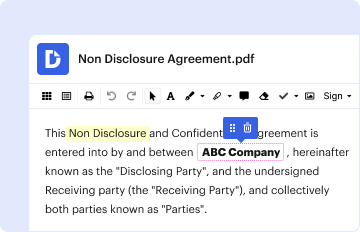
01. Edit your hs 1815 online
Type text, add images, blackout confidential details, add comments, highlights and more.
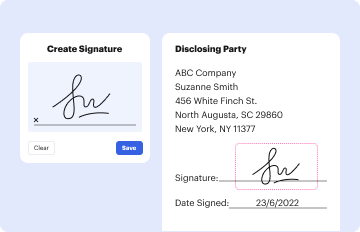
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
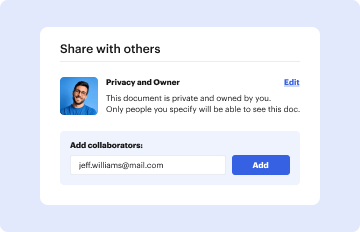
03. Share your form with others
Send hs1815 via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out HS 1815 HIPAA Authorization Form - PA Department of ... with DocHub

- Click ‘Get Form’ to open it in the editor.
- Begin by filling in your personal information in Section 1, including your name, date of birth, address, and ID number(s). This information is crucial for identifying the records you wish to disclose.
- In Section 2, specify the reason for disclosure. If it's at your request, simply state 'At the request of the individual.' Be clear about what information you want shared.
- Review the understanding section (Section 3) carefully. It outlines your rights regarding revocation and conditions related to treatment and payment.
- Complete Part A by detailing the specific information to be disclosed and the time period for which this information is relevant.
- If applicable, indicate whether drug and alcohol, mental health, or HIV/AIDS information should be disclosed in Part B. Make sure to check 'Yes' or 'No' as appropriate.
- Finally, sign and date the form. If a personal representative is signing on your behalf, include their relationship to you. Ensure a witness signs if required for certain disclosures.
Start using our platform today to easily complete your HS 1815 HIPAA Authorization Form online for free!
Fill out HS 1815 HIPAA Authorization Form - PA Department of ... online
It's free
It's free
See more HS 1815 HIPAA Authorization Form - PA Department of ... versions
We've got more versions of the HS 1815 HIPAA Authorization Form - PA Department of ... form. Select the right HS 1815 HIPAA Authorization Form - PA Department of ... version from the list and start editing it straight away!
| Versions | Form popularity | Fillable & printable |
|---|---|---|
| 2017 | 4.8 Satisfied (20 Votes) |
Got questions?
We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.
Contact us
How to get HIPAA authorization?
FormDr gives your business everything needed to easily send and receive HIPAA compliant forms online. Send patients your forms to fill out on their phone, tablet, or computer. Patients easily sign and submit completed forms securely online.
What is required on a HIPAA authorization form?
The name (or other specific identification) of the person or class of persons authorized to make the requested use or disclosure. The name(s) or other specific identification of the person or class of persons to whom information will be disclosed. A description of the purpose of the requested use or disclosure.
How do I fill out a HIPAA authorization form?
HIPAA is the Health Insurance Portability and Accountability Act of 1996. This law was passed as a way of protecting workers from losing their health insurance coverage when they change jobs or have a docHub event occur in their lives. It is not the same as the Cobra requirements of the early 1990s.
What is an example of a HIPAA authorization?
I hereby authorize use or disclosure of protected health information about me as described below. 4. I understand that the information used or disclosed may be subject to re-disclosure by the person or class of persons or facility receiving it, and would then no longer be protected by federal privacy regulations.
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more




