





Here's how it works
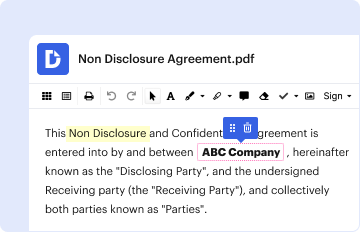
01. Edit your ins5140 online
Type text, add images, blackout confidential details, add comments, highlights and more.
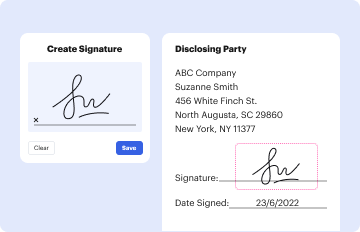
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
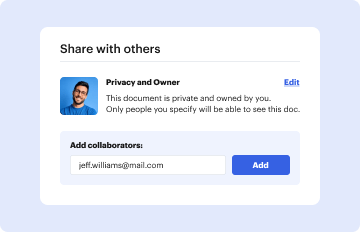
03. Share your form with others
Send ins5140 form via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out ins5140 with our platform

- Click ‘Get Form’ to open the ins5140 in the editor.
- In Section 1, enter your Social Insurance Number, Date of Birth, Last Name, First Name, and Initials. Fill in your Full Postal Address including Apt. No., Area Code Telephone Number, City or Town, Province/Territory, and Postal Code.
- Sign the form as the claimant or representative to authorize the release of information regarding your illness or pregnancy.
- Proceed to Section 2 where a medical doctor must complete details about your incapacity. They will need to provide dates related to your medical condition and expected recovery date.
- Ensure that the medical practitioner fills in their name, specialty, address, and signature along with their contact number and date.
Start using our platform today for free to easily fill out and manage your ins5140 form!
Fill out ins5140 online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


