





Here's how it works
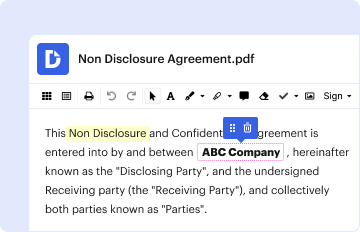
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
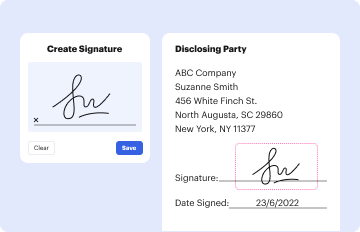
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
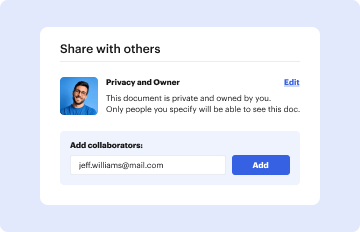
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Appeal Form -Member v5doc with our platform

- Click ‘Get Form’ to open the Appeal Form -Member v5doc in the editor.
- Begin by entering your Participant ID# and CIGNA Participant Name at the top of the form. This information is crucial for identifying your appeal.
- Fill in your Employer Name, Account Number, Patient Name, Date of Birth, and State of Residence. Ensure all details are accurate to avoid delays.
- In the section regarding the Health Care Professional or Facility Name, provide the relevant details about your healthcare provider.
- Indicate whether you are filing the appeal as a Participant, Primary Care Physician, or another representative. Specify your relationship to the participant if applicable.
- Clearly state the reason for your appeal by checking off the appropriate selection that describes your situation. Include any additional comments in the provided section.
- Attach any supporting documentation required for your appeal, such as medical records or previous claim letters.
- Finally, review all entered information for accuracy before submitting it through our platform.
Start using our platform today to easily complete and submit your Appeal Form -Member v5doc for free!
Fill out Appeal Form -Member v5doc online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more




